One App. Every Woman.
One App. Every Woman.
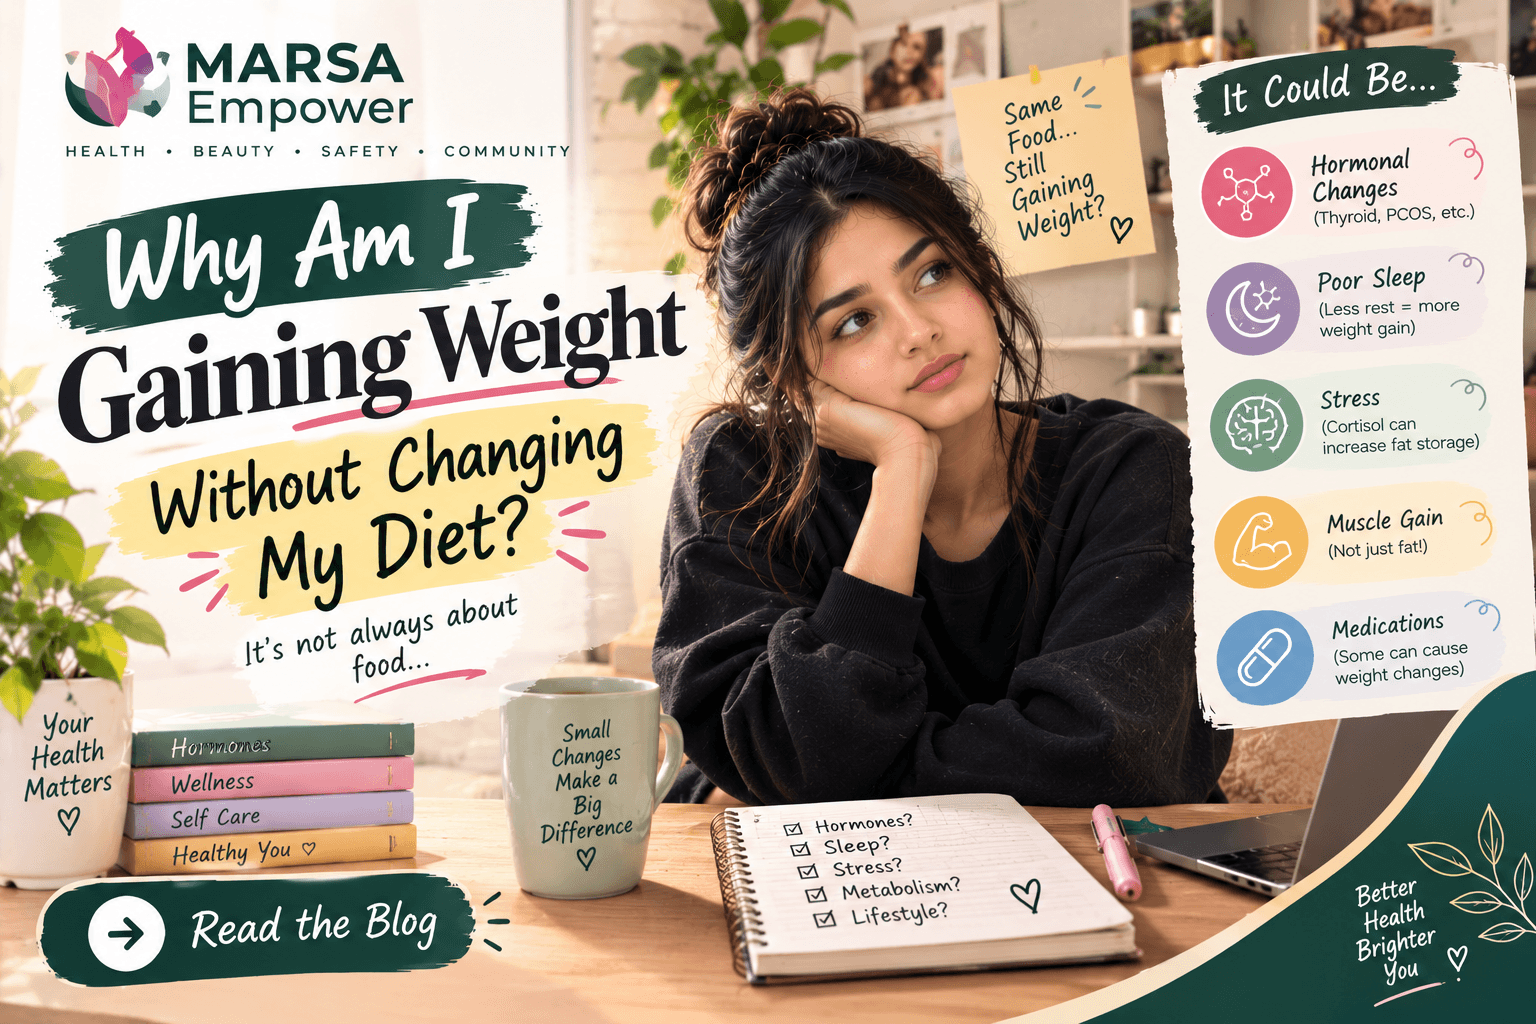
Discover the reasons behind unexpected weight gain without diet changes. Learn about hormonal, lifestyle, and medical factors and actionable tips.

Maryam Mumtaz
Co-Founder & CEO
13 min read•9/28/2026
Marsa Empower · Women's Health & Wellness · For Girls & Women Aged 13 and Above · 13 min read
You have not changed what you eat. You have not become less active. And yet the scale is moving upward — consistently, gradually, and without an explanation that seems adequate.
This experience is more common than most women realise — and more often than it should be, it is dismissed as a personal failing, attributed entirely to lifestyle, or told to a doctor only to be met with generic advice about eating less and moving more.
But weight gain that occurs without clear dietary or activity changes is not always a lifestyle problem. The female body is governed by a complex hormonal, metabolic, and neurological system whose disruption can produce weight changes that are genuinely not explained by food intake alone. Thyroid dysfunction, insulin resistance, PCOS, cortisol dysregulation, medication effects, fluid retention, and the hormonal transitions of puberty, pregnancy, perimenopause, and menopause all produce weight changes that are biological — not behavioural.
Understanding the difference between weight change that is expected and manageable, weight change that reflects a medical condition requiring investigation, and weight change that is simply a normal physiological fluctuation is the most important step toward responding appropriately.
This guide provides that understanding.
Yes. This is not a question of whether the laws of energy balance apply — they do. Weight gain occurs when energy intake exceeds energy expenditure over time. But the critical point is that both sides of this equation change in ways that are not always visible, conscious, or within personal control.
Metabolic rate can fall. The thyroid governs the metabolic rate of every cell in the body. When thyroid hormone is insufficient (hypothyroidism), the body burns fewer calories at rest — so the same dietary intake that previously maintained weight now produces a caloric surplus.
Energy expenditure can decrease without obvious changes. Reductions in non-exercise activity thermogenesis (NEAT) — the calories burned through incidental daily movement, fidgeting, standing, and other non-deliberate activity — can significantly reduce total daily caloric expenditure without any conscious reduction in exercise.
Water retention produces apparent weight gain. Fluid retention from hormonal changes, elevated cortisol, high salt intake, certain medications, or medical conditions produces real weight on the scale without any change in body fat.
Insulin resistance promotes fat storage. Elevated insulin levels — from insulin resistance in PCOS, pre-diabetes, or metabolic syndrome — direct more of the same dietary energy into fat storage rather than making it available for immediate use.
Cortisol promotes abdominal fat accumulation. Chronically elevated cortisol from stress directly promotes fat deposition around the abdomen, independently of total caloric intake.
So: yes, it is genuinely possible to gain weight without eating more — and understanding which of these mechanisms is relevant for a specific woman determines both what is causing the gain and what will meaningfully address it.
Not all weight changes require investigation or concern.
Normal weight fluctuation of one to three kilograms across a day or week is entirely normal and reflects changes in hydration status, the weight of food in the digestive tract, glycogen and associated water storage, and hormonal fluid retention. This is not true weight gain in the sense of increased body fat or meaningful change in body mass — it is the normal variability of a living biological system.
Premenstrual weight increase of one to three kilograms in the week before the period, followed by return to baseline after the period begins, is normal physiological fluid retention from hormonal changes — not meaningful weight gain.
Weight gain from a change in activity level following an injury, illness, or period of reduced physical activity is a direct consequence of reduced energy expenditure and is understandable and addressable.
Potentially significant unexplained weight gain is typically characterised by several features: it is progressive rather than fluctuating (the scale continues rising over weeks and months rather than going up and coming back down); it represents five percent or more of total body weight over six to twelve months; it is not explained by any identifiable change in dietary intake, activity level, or life circumstances; and it may be accompanied by other new symptoms suggesting an underlying cause.
One of the most common contributors to gradual weight gain that feels unexplained is a reduction in overall daily movement that is not consciously registered as a change in exercise. Starting a more desk-based job, working from home, driving instead of walking, spending more time on screens, recovering from an injury — all of these reduce caloric expenditure through reduced daily movement without requiring any change in conscious exercise habits.
The loss of incidental daily movement — walking to a bus stop, climbing stairs, moving around an office, housework — is difficult to perceive consciously but can reduce daily energy expenditure by several hundred calories.
Fluid retention from various causes — high dietary sodium, hormonal changes, certain medications, prolonged sitting or standing, or underlying medical conditions — produces temporary increases in scale weight that reflect water rather than fat. This type of weight gain typically fluctuates with circumstances rather than being consistent and progressive.
However, significant new fluid retention — particularly if it presents as visible swelling of the legs, feet, ankles, or face — warrants medical evaluation to identify the cause.
Oestrogen, progesterone, testosterone, cortisol, insulin, thyroid hormone, and other hormones all influence weight through their effects on appetite, metabolic rate, fat distribution, fluid balance, and energy storage. Any hormonal change — from natural life stage transitions, medical conditions, or medications — can produce weight changes that are not explained by dietary intake alone.
Psychological stress produces a specific and well-documented pattern of physiological changes that promote weight gain — discussed in detail in its own section below.
Consistent sleep insufficiency disrupts the hormonal regulation of appetite and energy metabolism in specific, measurable ways that increase caloric intake and promote fat storage — discussed in its own section below.
From the mid-thirties onward, muscle mass gradually declines (sarcopenia) unless actively maintained through strength training. Since muscle is more metabolically active than fat, this gradual muscle loss reduces the resting metabolic rate — meaning fewer calories are burned at rest with each passing year. When caloric intake stays the same but metabolic rate falls, a caloric surplus accumulates gradually and weight increases over time without any change in eating habits.
Any significant reduction in physical activity — from a sedentary period, injury, recovery from illness — reduces muscle mass that was previously being maintained by that activity. Less muscle mass means a lower metabolic rate and a reduced caloric requirement, creating the conditions for weight gain on an unchanged diet.
Small, gradual changes in eating patterns — slightly larger portions that feel the same, more frequent small snacks, higher-calorie beverage consumption, eating faster (which impairs satiety signals), more meals eaten while distracted — can accumulate to meaningful caloric increases over time without feeling like a dietary change. These are worth considering as part of any investigation of unexplained weight gain, alongside the medical and hormonal factors.
Hypothyroidism (underactive thyroid) is one of the most common and most consistently missed causes of unexplained weight gain in women. The thyroid produces hormones that regulate the metabolic rate of every cell in the body. When these hormones are insufficient, the body's calorie-burning capacity falls — sometimes significantly.
Weight gain from hypothyroidism is typically gradual, progressive, and resistant to the usual dietary adjustments that would otherwise slow it. It is characteristically accompanied by other hypothyroid symptoms: persistent heavy fatigue, cold intolerance, hair thinning, dry skin, constipation, and low mood. The outer third of the eyebrows may thin.
A TSH blood test identifies hypothyroidism. Thyroid conditions are five to eight times more common in women than men and are among the most consistently underdiagnosed causes of weight gain in women.
PCOS involves insulin resistance as a core metabolic mechanism in the majority of affected women. Elevated insulin signals fat cells to store more energy — directly promoting weight gain, particularly in the abdominal area — while simultaneously making weight loss significantly harder.
PCOS-related weight gain often occurs despite diet and lifestyle patterns that would not produce weight gain in women without insulin resistance. This is not a personal failing — it is the direct metabolic consequence of insulin signalling being disrupted in a way that biases the body toward fat storage.
Women with PCOS typically have additional symptoms: irregular or absent periods, persistent jawline acne, excess facial or body hair, scalp hair thinning, and fatigue.
As discussed in more detail below, the menstrual cycle produces predictable, cyclical weight fluctuations from hormonal fluid retention. These are not unexplained weight gain — they are expected physiological variation.
Pregnancy produces significant and appropriate weight gain. This is the most commonly expected reason for weight gain in reproductive-age women and deserves no further qualification here except to note that any woman with unexplained weight gain who is of reproductive age should consider pregnancy as a possibility if menstruation is delayed.
The hormonal changes of the menopausal transition — declining oestrogen, altered insulin sensitivity, changes in body fat distribution — produce one of the most consistent patterns of weight change in women's lives. The midlife weight gain that many women notice from their mid-to-late forties onward is primarily driven by these hormonal changes rather than dietary changes, and it preferentially affects abdominal fat distribution as oestrogen's previous protective effect on fat distribution is removed.
Premenstrual weight gain of one to three kilograms in the week before the period is one of the most common and most normal experiences in menstrual health. It is driven by progesterone's effect on fluid retention and by the bloating from digestive changes in the luteal phase, and it resolves naturally within a few days of the period beginning.
Because this cyclical gain and loss repeats monthly, comparing weight at different points in the cycle — weighing on day 27 and then on day 3 of the following cycle, for example — can make it appear that significant weight gain has occurred when in fact the difference is primarily fluid.
For this reason, body weight is most meaningfully compared at the same point in the menstrual cycle each month — for example, consistently in the first few days of the period when fluid retention is at its lowest — rather than at random times that may fall in different cycle phases.
A woman who weighs herself at different cycle phases and perceives a three-kilogram gain that is actually cyclical fluid retention may respond with anxiety and dietary restriction that is both unnecessary and counterproductive.
Yes — through a specific, well-documented physiological mechanism, not simply through stress-driven overeating (though that is also relevant for many women).
Chronic psychological stress elevates cortisol — the primary stress hormone produced by the adrenal glands. Elevated cortisol:
Promotes abdominal fat storage directly. Cortisol receptors in visceral (abdominal) fat cells are particularly responsive to cortisol signalling. Chronic cortisol elevation directly drives fat deposition in the abdominal area regardless of total caloric intake. This is the mechanism behind the characteristic "stress belly" pattern.
Increases appetite for calorie-dense, high-sugar, high-fat foods. Cortisol drives cravings for the foods the brain associates with quick energy and pleasure, increasing total caloric intake in ways that feel compulsive rather than chosen.
Worsens insulin resistance. Elevated cortisol reduces cellular insulin sensitivity, promoting more energy being stored as fat from the same caloric intake.
Disrupts sleep. Chronically elevated cortisol impairs sleep quality, which independently worsens appetite regulation.
These effects mean that chronic stress produces weight gain through multiple biological pathways simultaneously — and that managing stress is a genuine and direct component of weight management for women living under significant sustained pressure.
Sleep deprivation is one of the most consistently documented contributors to weight gain, and one of the most consistently overlooked.
When sleep is insufficient — consistently less than seven hours for most adult women — several hormonal changes occur that directly promote weight gain.
Ghrelin rises. Ghrelin is the primary hunger-stimulating hormone. Sleep deprivation significantly increases ghrelin levels, producing increased hunger — particularly for high-calorie, high-carbohydrate foods — that persists throughout the following day.
Leptin falls. Leptin is the primary satiety hormone. Sleep deprivation reduces leptin, impairing the sense of fullness after eating and promoting continued intake beyond actual caloric need.
Cortisol remains elevated. The cortisol that would normally fall during adequate sleep remains elevated with poor sleep, producing the abdominal fat promotion and insulin resistance effects described above.
Insulin sensitivity falls. Even one night of poor sleep measurably worsens next-day insulin sensitivity, promoting more energy being stored as fat.
The combined effect of these hormonal changes is a meaningful increase in appetite and a meaningful reduction in metabolic efficiency — producing weight gain even without any intentional dietary change. Women who are consistently sleep-deprived from any cause — screen use before bed, irregular schedules, care responsibilities for others — often find that weight management is significantly harder during these periods.
Several commonly used medications list weight gain as a documented side effect. Women who notice weight gain beginning after starting a new medication should consider this connection and discuss it with their prescribing doctor.
Antidepressants. Several antidepressants — particularly tricyclic antidepressants (TCAs), mirtazapine, and some SSRIs — are associated with weight gain through their effects on appetite, metabolism, or fluid balance.
Antipsychotics. Several antipsychotic medications produce significant weight gain through their effects on appetite, sedation, and metabolic function.
Corticosteroids. Prednisolone and other corticosteroids prescribed for inflammatory and autoimmune conditions cause fluid retention and appetite increases that produce significant weight gain with prolonged use.
Contraceptive hormones. Some hormonal contraceptives — particularly progestogen-dominant injectable methods and some combined pill formulations — can contribute to weight changes, primarily through fluid retention.
Diabetes medications. Some diabetes medications, particularly insulin and certain older oral agents, can produce weight gain through their effects on glucose metabolism.
Blood pressure medications. Some beta-blockers used for blood pressure and heart conditions are associated with modest weight gain.
Never stop prescribed medication without discussing it with a healthcare provider. However, if weight gain began after starting a specific medication, raising this with the prescribing doctor allows a conversation about whether alternative formulations or medications with less weight-gain tendency are appropriate.
Described above — one of the most common medical causes of unexplained progressive weight gain in women. Identified by TSH and free T4 blood tests. Treated with thyroid hormone replacement that, in most cases, restores metabolic rate and allows weight to be managed with normal lifestyle approaches.
Described above — insulin resistance driving fat storage and weight gain resistant to usual management approaches. Diagnosed through clinical assessment and blood tests. Managed through low-glycaemic dietary approaches, regular exercise, and medical treatment where indicated.
Cushing's syndrome results from chronically elevated cortisol — either from adrenal gland tumours, pituitary tumours, or long-term corticosteroid medication. It produces a distinctive pattern of weight gain: central abdominal obesity, fat accumulation at the back of the neck and face, relatively thin arms and legs, purple stretch marks, high blood pressure, blood sugar problems, and skin thinning. It is uncommon but important to consider when the clinical pattern suggests it.
Heart failure, kidney disease, liver disease, and lymphoedema can all produce significant fluid retention that presents as weight gain. These conditions are typically accompanied by other features — visible leg and ankle swelling, breathlessness, significant fatigue — that point toward their cause.
Weight gain during the teenage years is often a source of significant anxiety for girls and their families — and it is important to approach this topic with the sensitivity and accuracy it deserves.
Most weight gain in teenage girls during puberty and adolescence is entirely normal, expected, and biologically necessary. The oestrogen-driven increase in body fat percentage during puberty is part of healthy female development — it supports the hormonal function that enables menstruation, bone density development, and reproductive health. Girls who resist this weight gain through dietary restriction risk impaired development and significant health consequences.
Beyond the normal weight changes of puberty, teenage girls can experience the same hormonal causes of unexplained weight gain as adult women: emerging PCOS, thyroid dysfunction, and the effects of stress and sleep deprivation.
For teenage girls, the most important context for any conversation about weight is distinguishing normal developmental weight gain from medically significant unexplained weight gain — and ensuring that any weight management concern is handled with sensitivity to the elevated risk of disordered eating in this age group. Weight-loss advice or dietary restriction guidance is generally inappropriate for teenage girls without specific medical indication and professional guidance.
Weight gain during puberty is normal, necessary, and driven by healthy hormonal development. The increase in body fat and overall weight during this period is not excess weight — it is developmental change that should not be restricted.
In the reproductive years, cyclical weight fluctuation from the menstrual cycle is normal. Progressive weight gain over years without lifestyle change is more likely to have a medical or hormonal component worth investigating.
Weight gain in pregnancy is expected and appropriate. Postpartum weight return varies significantly between women. Significant weight that does not return toward pre-pregnancy levels over many months — particularly alongside other symptoms — may warrant thyroid and hormonal assessment.
The years before menopause are often when women first notice that weight management has become meaningfully harder than before. The combination of declining oestrogen, altered insulin sensitivity, increased cortisol responsiveness, and muscle mass changes produces the characteristic midlife weight change. Strength training, nutritional quality, and sleep and stress management are the most evidence-supported approaches for this life stage.
Post-menopause, the full hormonal effects on fat distribution and metabolic rate are established. The same principles apply — strength training is particularly important for maintaining the muscle mass and metabolic rate that support weight management.
Weight gain is normal and expected in the following circumstances.
During puberty — weight gain is a feature of healthy development. During pregnancy — appropriate weight gain in pregnancy is health-protective. In the premenstrual week — fluid retention of one to three kilograms is physiological. After a significant increase in strength training — muscle weighs more than fat, and initial muscle gain may increase scale weight while improving body composition. Following a period of significant underweight — restoring weight to a healthy range is appropriate. In the first few weeks after starting a new exercise programme — glycogen storage increases and water is retained in muscles.
Gaining several kilograms in a very short period — days to a couple of weeks — without any change in eating is more likely to reflect rapid fluid accumulation than fat gain. This warrants medical evaluation, particularly if accompanied by swelling.
Visible oedema — swelling from fluid accumulation in the tissues — alongside weight gain is a medical symptom that can indicate heart, kidney, or liver conditions, or significant hormonal changes. It warrants prompt evaluation.
Significant progressive weight gain alongside profound, persistent fatigue is a combination that strongly suggests hypothyroidism and warrants prompt thyroid function testing.
Weight gain accompanied by new irregularity or absence of periods points toward hormonal causes including PCOS or thyroid dysfunction and warrants gynaecological and endocrine assessment.
New breathlessness alongside weight gain may indicate fluid retention from a cardiac or respiratory condition and requires medical evaluation.
Any significant weight gain accompanied by other new systemic symptoms — purple stretch marks, high blood pressure, significant skin changes, neurological symptoms, or feeling generally unwell — warrants medical evaluation to identify an underlying cause.
Weigh once per week at the same time of day and in the same menstrual cycle phase. This creates a meaningful trend rather than a snapshot that reflects daily fluctuation. Two to three months of consistent tracking reveals whether weight is genuinely and progressively increasing or simply fluctuating normally.
Honestly assess whether total daily movement has changed — including incidental activity, not only deliberate exercise. Wearable step-counting devices reveal whether daily steps have fallen significantly from previous levels.
Seven to nine hours of consistent, quality sleep per night addresses one of the most direct and most correctable hormonal contributors to weight gain. Screen-free wind-down time, consistent sleep timing, and a bedroom environment that supports sleep are the most impactful starting points.
Regular physical activity (the most effective cortisol-lowering intervention available), adequate sleep, breathwork, social connection, and professional support for significant stress or anxiety all directly reduce the cortisol burden that promotes abdominal weight gain.
Rather than dramatic dietary restriction — which elevates cortisol and worsens the hormonal environment that drives stress-related weight gain — focus on nutritional quality. Reducing high-glycaemic foods and sugary drinks, increasing protein and fibre at meals for improved satiety, and maintaining consistent meal timing all support metabolic health without creating the restriction-stress cycle.
Very low-calorie diets produce metabolic adaptation that reduces the resting metabolic rate — the body down-regulates its calorie-burning capacity in response to severe restriction. This makes weight management harder over time, not easier.
Arrange a medical appointment if weight gain meets any of the following criteria.
Weight gain is progressive over weeks to months without identifiable lifestyle explanation. Weight gain is accompanied by significant fatigue, cold intolerance, hair changes, constipation, or dry skin (suggesting hypothyroidism). Weight gain is accompanied by irregular or absent periods, persistent acne, excess facial hair, or scalp thinning (suggesting PCOS). Visible swelling of the legs, feet, or face accompanies weight gain. Weight gain is accompanied by shortness of breath or feeling generally very unwell. You began a new medication when the weight gain started. Weight is concentrated unusually around the abdomen with relatively thin limbs and you have high blood pressure and skin changes (suggesting possible Cushing's syndrome). You are a teenager and weight gain is significantly affecting quality of life, mood, or menstrual health.
The initial blood tests most relevant to unexplained weight gain in women typically include:
Thyroid function testing (TSH and free T4) — the most important first investigation. Fasting blood glucose and fasting insulin — to assess insulin resistance and diabetes. Full blood count — to assess for anaemia and general health. Hormone profile where PCOS is suspected — testosterone, SHBG, LH, FSH, and prolactin. Cortisol testing where Cushing's syndrome is considered. Liver and kidney function tests where fluid retention warrants investigation. Cholesterol profile — often altered by the same metabolic conditions that cause weight gain.
A pelvic ultrasound may be requested if PCOS or other pelvic conditions are suspected.
Marsa's Health Hub allows women to track their weight, energy levels, sleep quality, stress, and other daily health patterns over time. This builds the documented pattern that is most useful for distinguishing normal fluctuation from progressive, medically significant weight change — and for providing specific, dated information at healthcare consultations.
Understanding where in the menstrual cycle a weight measurement falls is essential for interpreting weight changes accurately. Marsa's cycle tracking allows women to consistently measure weight at the same cycle phase each month, eliminating the confusion of comparing premenstrual fluid retention to post-period baseline.
For women with known hormonal conditions including PCOS or hypothyroidism, Marsa's tracking tools allow monitoring of weight, energy, cycle regularity, and symptoms over time — providing the long-term view that makes the effects of management changes visible.
Marsa's educational resources explain the hormonal, metabolic, and lifestyle factors that drive weight changes in women — providing the knowledge base that helps women understand whether their weight change has a likely identifiable cause and whether it warrants professional investigation.
Marsa's AI health guidance through Digital Doctors provides educational information on weight changes, their possible causes, and when medical evaluation is the appropriate next step.
Important note. Marsa Empower is a health education and wellness companion. Medical causes of unexplained weight gain — including thyroid disorders, PCOS, and Cushing's syndrome — require clinical evaluation, blood testing, and management by a qualified healthcare professional. Marsa helps women prepare for and understand that process.
Why am I gaining weight even though I eat the same amount?
Several factors can produce weight gain without any change in dietary intake. Thyroid dysfunction reduces metabolic rate so the same intake produces a caloric surplus. Insulin resistance from PCOS or pre-diabetes promotes more energy being stored as fat. Reduced daily activity reduces total energy expenditure. Stress-elevated cortisol promotes abdominal fat accumulation. Poor sleep disrupts appetite hormones. Fluid retention increases scale weight without fat gain. Blood tests including thyroid function and fasting glucose are the most appropriate first investigation for persistent unexplained weight gain.
Can hormones cause unexplained weight gain?
Yes. Hypothyroidism, PCOS, Cushing's syndrome, elevated cortisol from chronic stress, insulin resistance, and the hormonal transitions of perimenopause and menopause all produce weight changes through specific biological mechanisms rather than changes in dietary intake. These are not lifestyle failures — they are hormonal conditions that deserve appropriate medical investigation and management.
Can my period make me gain weight?
The premenstrual phase — approximately the week before the period begins — produces cyclical fluid retention of one to three kilograms from hormonal changes. This is normal, temporary, and resolves within a few days of the period beginning. It is not true fat gain and does not require management beyond awareness that it is a normal monthly variation.
Can lack of sleep cause weight gain?
Yes. Sleep deprivation elevates ghrelin (hunger hormone), reduces leptin (satiety hormone), elevates cortisol, and worsens insulin sensitivity — producing increased appetite, reduced satiety, and increased fat storage from the same caloric intake. Consistently sleeping seven to nine hours per night addresses one of the most direct and correctable hormonal contributors to weight gain.
Why am I gaining weight around my stomach?
Abdominal weight gain specifically is most commonly associated with elevated cortisol (from stress or Cushing's syndrome), insulin resistance (from PCOS or pre-diabetes), and the redistribution of fat toward the abdomen that occurs at menopause as oestrogen declines. All of these have identifiable causes and specific management approaches.
Can stress cause weight gain?
Yes. Chronic psychological stress elevates cortisol, which directly promotes abdominal fat accumulation, worsens insulin resistance, increases appetite for calorie-dense foods, and disrupts sleep — all of which drive weight gain through biological pathways that are not simply explained by stress-related overeating.
When should unexplained weight gain worry me?
Unexplained weight gain warrants medical evaluation when it is progressive over weeks to months without lifestyle explanation, accompanied by other new symptoms (fatigue, cold intolerance, menstrual changes, visible swelling, shortness of breath), concentrated unusually around the abdomen, or affecting a teenager's health or quality of life.
How can I stop gaining weight without following a strict diet?
Focus on sustainable changes rather than restriction: consistent sleep, stress management, regular physical activity including strength training, balanced nutritious meals with adequate protein and fibre, reduced high-glycaemic foods and sugary drinks, and investigation of any hormonal causes if present. These changes address the biological drivers of weight gain rather than imposing restriction that worsens them.
Weight gain that occurs without obvious dietary change is not automatically explained by hidden eating or insufficient effort. The female body is governed by a complex hormonal and metabolic system whose disruption — from thyroid dysfunction, insulin resistance, stress, poor sleep, medication effects, or the natural hormonal transitions of different life stages — produces weight changes that are biological, not behavioural.
Taking unexplained weight gain seriously, documenting its pattern, considering its possible causes, and investigating appropriately with blood tests and clinical assessment is the most productive response. Dismissing it as a personal failing or responding with increasingly restrictive dieting that worsens the underlying hormonal disruption is the least productive one.
Track the pattern. Understand the possible causes. Address the modifiable factors. And when progressive, unexplained weight gain persists despite appropriate lifestyle attention, seek the medical investigation that may reveal a treatable cause.
Your weight change may be telling you something. It deserves to be heard and properly investigated — not ignored, and not simply treated with willpower.
Educational Disclaimer
This article is for educational and awareness purposes only. It does not constitute medical advice, diagnosis, or treatment. If you have experienced significant, unexplained, or persistent weight gain — especially if accompanied by other symptoms — please consult a qualified healthcare professional for personalised evaluation and guidance.
Marsa Empower | Care. Safety. Growth.
Visit marsaempower.com to track your weight, health patterns, and menstrual cycle, access women's health education, and explore wellness resources at every stage of life.
Medical Disclaimer
This article is for general informational and educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay seeking it because of something you have read on MARSA Empower.
Written By
Maryam Mumtaz
Co-Founder & CEO
Co-Founder of MARSA Empower who leads the visual and strategic evolution of the platform. Maryam bridges technical complexity with human-centric design, architecting the team's official roadmap and ensuring MARSA effectively addresses the real-world needs of women. With deep expertise in agentic AI, full-stack development, and UI/UX design, she has delivered 50+ projects for 30+ satisfied clients.
Enjoyed this story?